Advancing Type 1 Diabetes Research
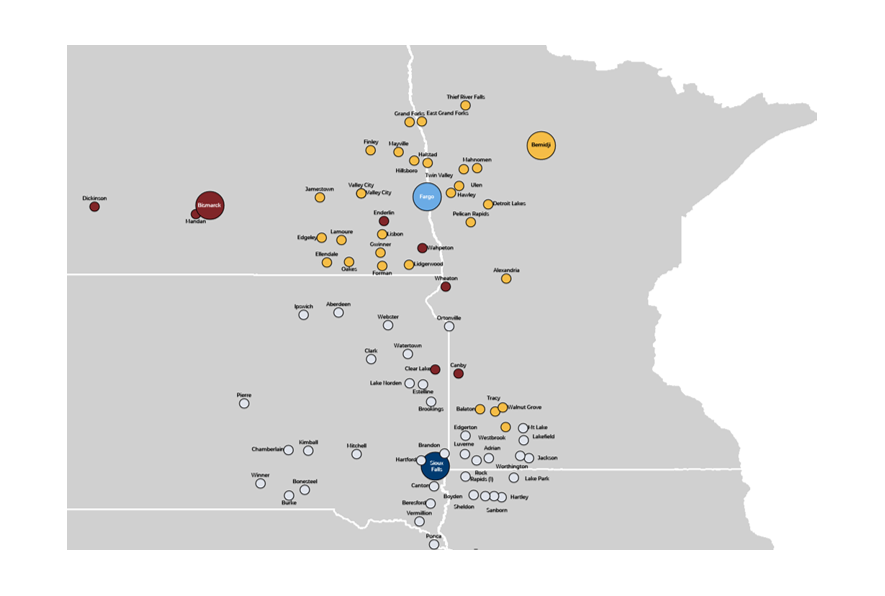
From 2020 to 2026, Sanford Health offered general population screening for type 1 diabetes and celiac autoantibodies through the PLEDGE study (Population Level Estimate of type 1 Diabetes risk Genes in Children) to Sanford patients 0-6 years & 9-16 years throughout the Sanford footprint. The PLEDGE study enrolled >17,000 children and continues to collect screening labs from enrolled children until [dec 2026]. Results from the PLEDGE study will be critical to support inclusion of these tests in standard pediatric screening recommendations.
The central innovation in PLEDGE was the integration of study procedures into routine pediatric care across all Sanford clinics. The PLEDGE study demonstrated feasibility in large-scale screening, and the ability to identify children at risk for T1D and enroll them into ongoing monitoring studies. The success of this integration and impact led to the development of a clinical T1D screening program, modeled after the PLEDGE study.
Why screen for type 1 diabetes?
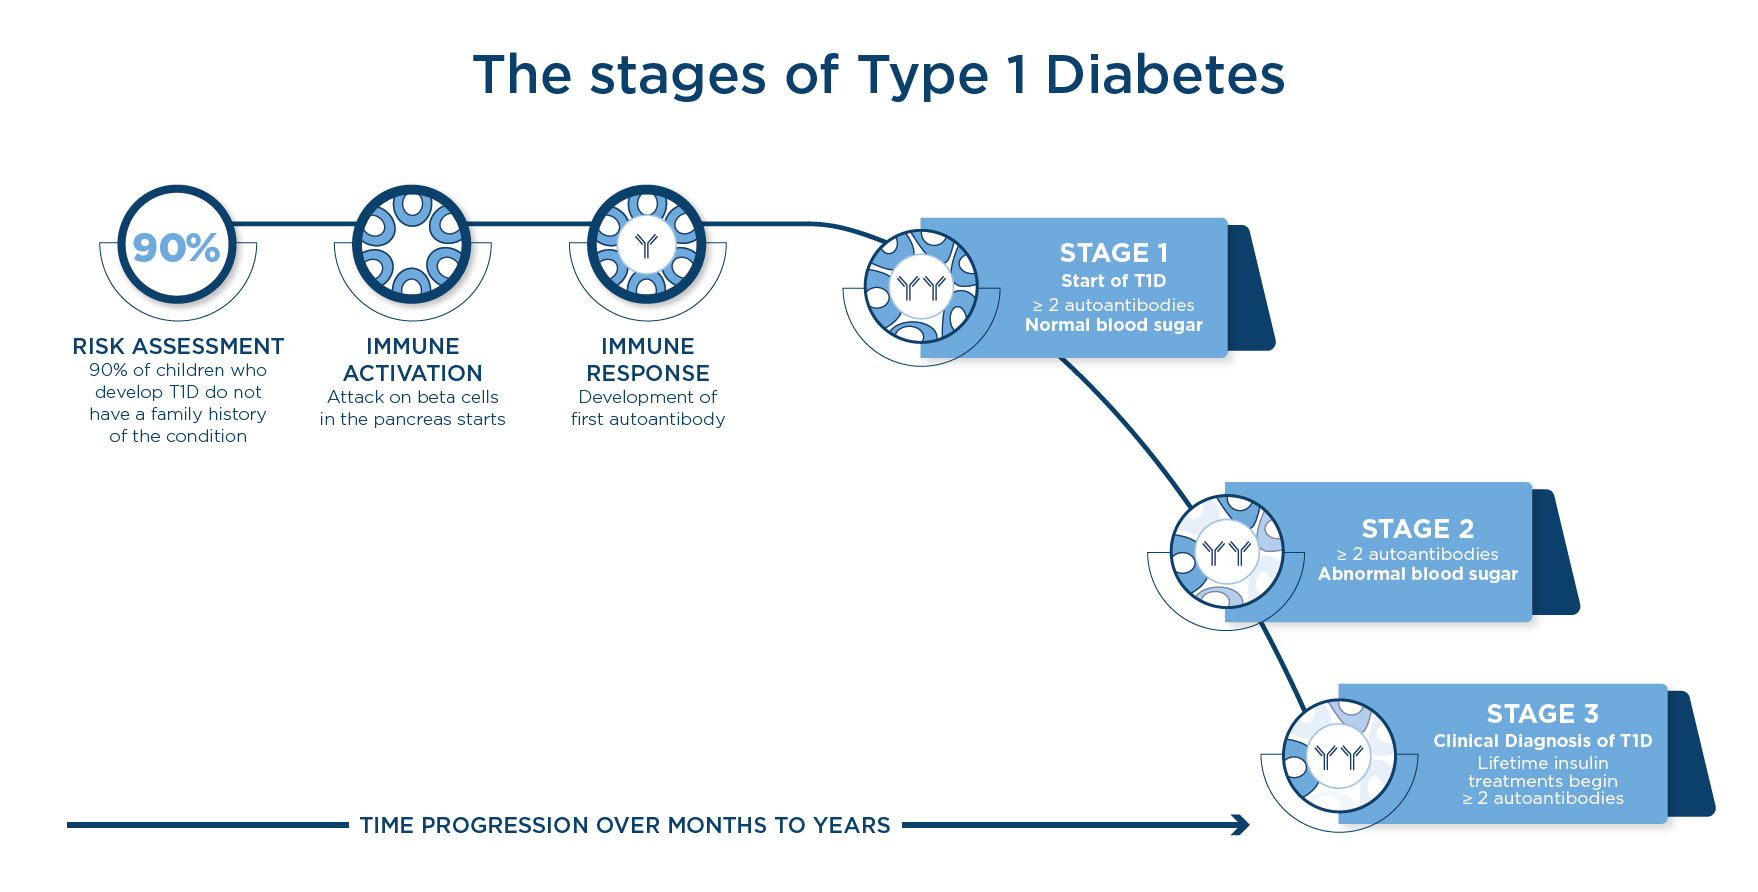
Type 1 diabetes results from autoimmune destruction of pancreatic beta cells that produce insulin. At the centennial of insulin’s discovery, it remains the mainstay of treatment but does nothing to address autoimmunity. There are other drugs currently in development, and with approval of teplizumab for Stage 2 T1D, we have the first drug targeting the autoimmunity causing T1D, along with additional drugs currently in development. However, for any interventions to be used, we need to identify who might benefit from these therapies.
The majority of children who develop T1D, present at a late stage with diabetic ketoacidosis (DKA), necessitating hospitalization and intensive care. DKA at presentation is associated with worse long-term glycemic control and cognitive deficits compared to those who were able to start insulin earlier and avoid DKA. Preventing initial DKA would be expected to decrease long-term complications with associated morbidity, mortality and related healthcare costs.
Hyperglycemia develops after a long period of autoimmunity, providing a window of opportunity to identify children at higher risk of progressing to overt diabetes. Early identification and family awareness can enable ongoing monitoring and appropriate testing so that insulin can be started early enough to prevent serious illness.
General population pediatric T1D screening has been shown in the ASK and Fr1DA studies to reduce the rate of DKA at presentation from 60% to ~3%. In the long term, identifying these high-risk children will enable trials of prevention therapies. In the meantime, there are significant benefits to preventing DKA at presentation.
Why screen all children?
Most screening efforts have focused on family members of people living with T1D. However, 90% of people with T1D do not have a family history for the disease. Programs to offer screening more widely – such as the Fr1da and ASK studies – have relied on clinical research staff to recruit children from clinics, an approach that is costly and difficult to scale. For eventual acceptance into standard primary care, any population-based screening tool must be simple, reliable, cost-effective and easily implemented when children are present for routine visits.
Screening process in the PLEDGE study
Anti-islet antibodies were collected at routine clinic appointments at about 2 years and again at about 5 years of age, and/or between 9-16 years of age. At the latter screenings, celiac antibodies were also collected, the inclusion of which has shown increased family engagement in other T1D screening programs. With the first sample collected, a blood spot for a targeted SNP-based genetic risk score (GRS) was also taken. For children enrolled prenatally, this was collected simultaneously with routine newborn screening samples.

Critical to the success of this project was the innovative use of the electronic health record and its associated patient messaging tools. Sanford Health leveraged these platforms to automate invitations to participate, enable documentation of consent, administer participant surveys, enter orders, and return results.
The success of PLEDGE has relied on the existing infrastructure of Sanford’s integrated health system. Labs were collected at routine clinic visits, specimens were sent to hub laboratories and sent to Sanford’s central lab for batching, processing and shipping to reference labs.
Children with T1D-related antibodies
Children identified to have persistent T1D autoantibodies are offered ongoing education, monitoring, and enrollment in appropriate intervention trials.
Monitoring is tailored to the individual’s risk, with periodic measurements of autoantibody status and glycemic control. Throughout the monitoring process, we maintain communication with the primary care team and the shared electronic health record is flagged for easy recognition of antibody positive children to encourage appropriate testing in case they present for care with T1D symptoms.
Sanford Pledge Sites